Disease
Common Eye Diseases: Early Symptoms, Prevention, and Treatment Options
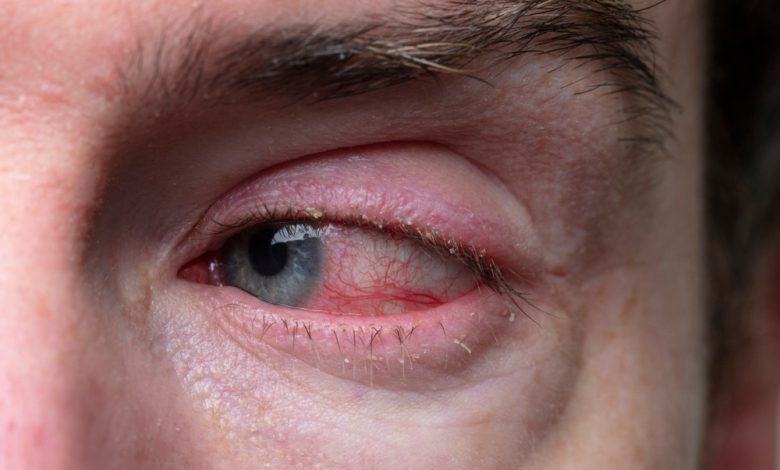
Most people consider vision to be the sensory function they fear losing above all others, yet eye care remains one of the most frequently postponed aspects of preventative medicine. The biological design of human vision makes this neglect particularly hazardous: the visual cortex possesses a remarkable capacity to compensate for gradual sensory deficits. When microvascular changes erode retinal capillaries or intraocular pressure degrades optic nerve fibers, the brain routinely stitches together fragments of the visual field, masking subtle blind spots until extensive, irreversible damage has already occurred.
Sustaining clear vision over a lifetime requires looking past the misconception that good vision simply means having 20/20 visual acuity on a distant wall chart. True ocular health depends on the structural integrity of the lens, retina, optic nerve, and microvasculature. Understanding the physiological mechanisms behind the most prevalent ocular disorders—and recognizing their subtle earliest clues—empowers individuals to protect their eyesight before symptoms disrupt daily life.
Glaucoma: The Silent Threat to the Optic Nerve
Glaucoma refers to a cluster of progressive optic neuropathies characterized by the structural loss of retinal ganglion cells and corresponding visual field deficits. In most presentations, this neurodegeneration is intimately tied to elevated intraocular pressure, which builds when the eye’s internal fluid, known as aqueous humor, fails to drain efficiently through the trabecular meshwork.
Subtle Presentations and Emergency Scenarios
The overwhelming majority of patients develop primary open-angle glaucoma, a chronic condition that progresses without pain, redness, or early sensory cues. The loss of sight begins at the outer periphery of the visual field, creeping inward so gradually that individuals often do not notice functional deficits until their sight narrows into tunnel vision.
In sharp contrast, acute angle-closure glaucoma occurs when the iris is pushed or pulled forward, abruptly blocking the drainage canals. This medical emergency manifests rapidly with severe ocular pain, profound headaches, blurred vision, rainbow halos surrounding bright light sources, and intense nausea. Immediate clinical intervention is imperative to prevent permanent blindness within hours.
Prevention and Clinical Management
Because mechanical damage to the optic nerve cannot be reversed, management centers on lowering intraocular pressure to a personalized target level that arrests further nerve deterioration.
-
Topical hypotensive medications: Daily prescription eye drops, including prostaglandin analogs and beta-blockers, remain the primary defense to either enhance fluid outflow or decrease aqueous humor production.
-
Laser therapies: Selective laser trabeculoplasty offers a non-invasive outpatient option that stimulates the drainage tissue, often reducing or eliminating dependence on daily drops.
-
Surgical intervention: When drops and laser treatments prove insufficient, surgeons deploy minimally invasive glaucoma surgery or traditional filtration procedures, such as trabeculectomy, to establish alternative outflow pathways.
Cataracts: Progressive Clouding of the Crystalline Lens
The crystalline lens inside the eye consists predominantly of water and specialized structural proteins known as crystallins, organized in a precise cellular architecture that allows light to pass through unobstructed. As tissue ages, these proteins denature, degrade, and aggregate, gradually turning a clear lens into an increasingly opaque, yellowish-brown barrier.
Early Warning Signs
Cataracts develop over years, frequently masquerading as ordinary refractive changes:
-
Needing brighter, more focused illumination to read comfortably.
-
Decreased contrast sensitivity, where colors appear faded, washed out, or tinged with yellow.
-
Increased glare and starburst rings around headlights during nighttime driving.
-
A phenomenon termed second sight, where reading vision temporarily sharpens as the central lens hardens and changes the eye’s focal point, shortly before overall visual acuity deteriorates.
Prevention and Restorative Surgery
While age remains the leading contributing factor, oxidative stress accelerates protein clumping. Minimizing environmental risk requires wearing sunglasses that block 100 percent of UVA and UVB rays, eliminating tobacco smoke exposure, and carefully managing blood glucose levels.
When cataracts impair independent living, surgical removal is the only definitive cure. Modern cataract extraction utilizes high-frequency ultrasound to break down the cloudy lens before vacuuming the fragments through a micro-incision. The natural lens is then replaced with an intraocular lens, which can be customized with monofocal, toric, or multifocal optics to simultaneously correct pre-existing astigmatism and presbyopia.
Age-Related Macular Degeneration: Defending Central Clarity
Age-related macular degeneration attacks the macula, the highly sensitive central portion of the retina responsible for sharp, straight-ahead vision necessary for reading, driving, and recognizing faces.
Dry Versus Wet Presentations
The condition originates in the dry form, distinguished by the accumulation of cellular waste products, called drusen, beneath the retinal pigment epithelium. Over time, these deposits starve the overlying photoreceptors, leading to gradual geographic atrophy and patchy blind spots directly in the center of the visual axis.
Roughly ten percent of these cases advance to wet macular degeneration, an aggressive stage characterized by choroidal neovascularization. Here, abnormal, fragile blood vessels sprout beneath the retina, leaking lipids, fluid, and blood into delicate retinal layers. This leakage causes abrupt visual distortion; straight lines—such as door frames, window blinds, or lines of text—appear bent, wavy, or discontinuous.
Intervention and Nutrition
Individuals with intermediate dry macular degeneration often benefit from specialized dietary formulations developed in extensive clinical trials, which combine high doses of vitamins C and E, zinc, copper, lutein, and zeaxanthin to slow disease progression. For dry macular degeneration that has advanced to geographic atrophy, newly approved complement-inhibitor medications administered via intravitreal injections can slow tissue decay.
For wet macular degeneration, treatment has been transformed by anti-vascular endothelial growth factor injections. These targeted therapeutics inhibit the signaling protein responsible for aberrant vessel proliferation, stopping fluid leakage, stabilizing central vision, and occasionally restoring clarity when administered promptly.
Diabetic Retinopathy: Microvascular Damage to the Retina
Diabetic retinopathy represents a major vascular complication of chronic hyperglycemia, affecting both type 1 and type 2 diabetics. Elevated circulating glucose damages the fragile endothelial cells lining the retinal capillaries, compromising their structural integrity.
In its initial non-proliferative stages, capillary walls balloon into microaneurysms and leak serum into surrounding tissues, which often culminates in diabetic macular edema—a swelling of the macula that constitutes the primary driver of vision loss in diabetic individuals. If capillary closure starves large sections of the retina of oxygen, the tissue responds by triggering proliferative diabetic retinopathy, producing a chaotic web of fragile new blood vessels. These vessels readily rupture, spilling blood into the vitreous gel and spawning fibrous scar tissue that can pull the retina away from its underlying support structure.
Diligent glycemic management, blood pressure regulation, and regular lipid monitoring form the biological foundation of prevention. Clinical treatments parallel those used for macular degeneration, leaning on intravitreal anti-VEGF injections, focal laser coagulation to seal leaking microaneurysms, and panretinal photocoagulation to shrink abnormal vascular networks.
Everyday Strategies for Sustained Eye Health
While advanced pharmacology and microsurgery provide remarkable restorative options, preserving lifelong optical health begins with disciplined daily protective habits:
-
Undergo dilated eye evaluations: A standard vision screening only assesses visual clarity at a fixed distance. A dilated examination allows a clinician to examine the peripheral retina, retinal vasculature, and optic nerve head for asymptomatic pathologies.
-
Practice ocular ergonomics: Extended screen use drops blink rates by more than half, prompting rapid tear film evaporation and ocular strain. Adhering to the 20-20-20 rule—pausing every 20 minutes to gaze at an object 20 feet away for 20 seconds—relaxes the ciliary muscles and redistributes the protective lipid layer of the tear film.
-
Incorporate physical protection: Beyond UV-rated sunglasses, using high-impact polycarbonate eyewear during home improvement projects, yard work, and racquet sports eliminates acute mechanical trauma, which remains a leading cause of unilateral visual impairment.
Vision loss is rarely an inevitable tax on aging. By pairing structured clinical screenings with an informed understanding of vascular and neurological symptoms, you transform eye care from an anxious reaction into an enduring, preventative safeguard.